VPDC

Diseases

What is RSV?Updated 9-17-2026
  • Respiratory Syncytial Virus (RSV) is a respiratory virus that spreads through the air and by touching surfaces or objects that have the virus on them.
  • Immunizations are available that can protect infants, children, and older adults from severe RSV illness.
RSV Facts Flyer

Fact Sheet

Currently being updated (9/14/26)
RSV Symptoms

People with RSV infection typically have the following symptoms:

  • Fever
  • Cough
  • Runny nose
  • Wheezing
  • In very young infants: increased irritability and difficulty breathing

Infants, older adults, and those with chronic heart or lung disease, weakened immune systems and underlying medical conditions, are at higher risk of severe illness.

How does RSV Spread?

RSV spreads from person to person through:

  • Direct Contact — Having close physical contact with an infected individual, such as kissing a child or person on the face.
  • Contaminated Surfaces — Touching hard or soft objects (like doorknobs, toys, and counters) that have the virus on them, and then touching your own eyes, nose, or mouth before washing your hands.
  • Airborne Droplets — Inhaling respiratory droplets released into the air when a sick person coughs or sneezes nearby.

People who have an RSV infection are usually contagious for 3 to 8 days, but sometimes infants and people with weakened immune systems can continue to spread the virus for as long as 4 weeks.

Information for the Public
Immunization Information

RSV immunization can help protect people from severe RSV illness. There are two types of RSV immunizations: RSV vaccines and long-acting RSV monoclonal antibodies.

For Older Adults:

Three RSV vaccines are available for adults ages 50 years and older:

There is no preference for one RSV vaccine over another.

  • RSV vaccine is given as one dose and is not an annual vaccine.
  • People who have already received an RSV vaccine should not receive another dose at this time.
  • RSV vaccine can be given at any time of year, but the best time is in late summer or early fall, before RSV season begins.
  • RSV vaccine can be given at the same visit as other vaccines.

See Immunization Recommendations below to learn who should receive an RSV vaccine.


For Pregnant People:

  • ABRYSVO (Pfizer) is the only RSV vaccine recommended for use during pregnancy to protect infants from severe RSV illness.
  • RSV vaccination during pregnancy helps protect the baby during their first RSV season.

See Immunization Recommendations below to learn which pregnant people should receive the RSV vaccine and when.


For Infants & Toddlers:

  • Long-acting RSV monoclonal antibodies help protect infants and young children from severe RSV illness. They are not vaccines, but they protect against RSV in a similar way by providing ready-made antibodies.
  • For most infants, either maternal RSV vaccination during pregnancy or an RSV monoclonal antibody given to the infant is enough to protect against severe RSV illness. Most infants do not need both.

Infants Younger Than 8 Months:

Two long-acting RSV monoclonal antibodies are available:

There is no preference between nirsevimab and clesrovimab for infants younger than 8 months.

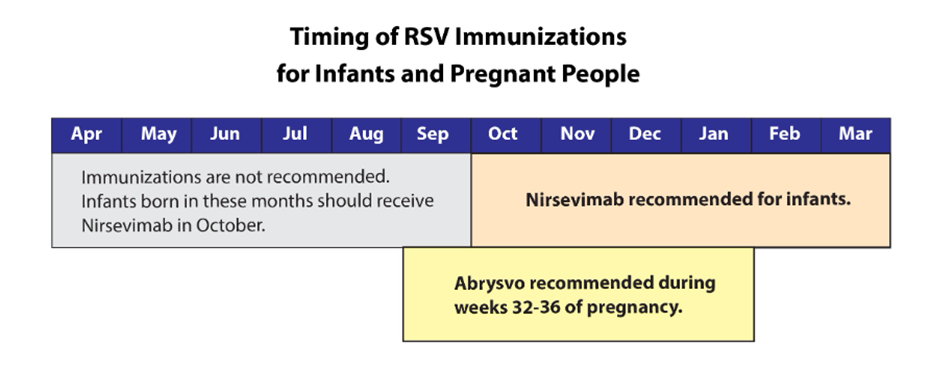
In California, RSV antibodies are typically given from October through March:

  • Eligible infants born October through March should receive an RSV antibody within one week after birth, ideally during the birth hospitalization.
  • Eligible infants born April through September should receive an RSV antibody as soon as possible on or after October 1st.

See Immunization Recommendations below to learn which infants should receive an RSV antibody.

Children 8–19 Months at Higher Risk for Severe RSV:

Nirsevimab (BEYFORTUS™) is available for certain children ages 8–19 months who are at increased risk for severe RSV illness and are entering their second RSV season.

  • In California, eligible children should receive nirsevimab as early as possible between October and March.
  • Clesrovimab (ENFLONSIA™) is not recommended for children ages 8–19 months.

See Immunization Recommendations below for conditions that may put a child at higher risk for severe RSV illness. Talk with your health care provider if you are not sure whether your 8–19-month-old child should receive nirsevimab.

Note: The recommended period for RSV immunization may sometimes extend beyond March based on RSV activity in California. If your infant is due to receive an RSV monoclonal antibody near the end of the recommended period, talk with your health care provider about the recommendations for the current RSV season.

See Immunization Recommendations below to learn which children should receive nirsevimab.

Getting Other Vaccines at the Same Visit

RSV immunizations can be given at the same visit as flu, COVID-19, and other recommended vaccines, when appropriate for the person’s age and eligibility.

How well do RSV immunizations work?

RSV immunizations lower the risk of severe RSV illness. How well they work may vary based on a person’s age, health, and how much time has passed since immunization.

  • According to the American Academy of Family Physicians (AAFP), all three RSV vaccines—AREXVY, ABRYSVO, and mRESVIA—provide adequate protection against severe RSV illness in adults ages 60 years and older.
  • RSV vaccination during pregnancy is at least 70% effective in preventing RSV-related hospitalizations in infants.
  • Nirsevimab (BEYFORTUS™) is at least 80-90% effective in preventing RSV-related hospitalizations in infants. Studies also shown that clesrovimab (ENFLONSIA™) has similar effectiveness.
Possible Vaccination Side Effects

Side effects from RSV vaccine are usually mild and temporary. They may include:

  • Redness, swelling, and pain at the site where the vaccine was given
  • Fatigue
  • Fever
  • Headache
  • Nausea
  • Diarrhea
  • Muscle or joint pain
Immunization Recommendations

The Los Angeles County Department of Public Health endorses California Department of Public Health's (CDPH) respiratory virus season immunization recommendations. This guidance was developed in collaboration with California partners in the West Coast Health Alliance and informed by national medical groups, including the American Academy of Family PhysiciansAmerican Academy of Pediatrics, and American College of Obstetricians and Gynecologists.

RSV immunization recommendations depend on a person's age, pregnancy, health conditions, and risk for severe RSV illness.

Who SHOULD get immunized
Older Adults

RSV vaccine is recommended for:

  • All adults 75 years and older
  • Adults 50–74 years old with the following medical and other conditions who are at increased risk of severe RSV illness.

People may be at higher risk if they:

  • Have chronic heart or lung disease (e.g., heart failure, coronary artery disease, congenital heart disease, chronic obstructive pulmonary disease, emphysema, asthma, interstitial lung disease, cystic fibrosis). Excludes isolated hypertension.
  • Have end-stage renal disease or dependence on hemodialysis or other renal replacement therapy
  • Have neurologic or neuromuscular conditions causing impaired airway clearance or respiratory muscle weakness (e.g., post-stroke dysphagia, amyotrophic lateral sclerosis, muscular dystrophy). Excludes history of stroke without impaired airway clearance.
  • Have chronic liver disease (e.g., cirrhosis)
  • Have chronic hematologic conditions (e.g., sickle cell disease, thalassemia)
  • Have a weakened immune system
  • Have certain other medical conditions, such as diabetes or obesity (body mass index ≥ 40 kg/m2)
  • Live in a nursing home or long-term care facility

Pregnant People

One dose of ABRYSVO (Pfizer) is recommended for pregnant people who are at 32 – 36 weeks gestation between September 1st and March 1st.

If ABRYSVO (Pfizer) was received during a previous pregnancy, another dose is not recommended during a later pregnancy. Instead, the infant should receive a long-acting RSV monoclonal antibody for protection against severe RSV illness.

Infants Younger Than 8 Months

One dose of a long-acting RSV monoclonal antibody (nirsevimab [BEYFORTUS™] or clesrovimab [ENFLONSIA™]) is recommended for infants younger than 8 months who are born during or entering their first RSV season if:

  • Their birthing parent did not receive a maternal RSV vaccine during the current pregnancy
  • The birthing parent's RSV vaccination status is unknown; or
  • Less than 14 days passed between RSV vaccination during pregnancy and the infant's birth.

Most infants born 14 or more days after maternal RSV vaccination do not need an RSV monoclonal antibody.

Children 8–19 Months

One dose of nirsevimab (BEYFORTUS™) is recommended for certain children ages 8–19 months who are at higher risk for severe RSV illness and are entering their second RSV season.

This includes:

  • Children with chronic lung disease of prematurity
  • Children with a weakened immune system
  • Children with severe cystic fibrosis
  • American Indian or Alaska Native children
  • children born preterm, at <32 weeks gestation, regardless of the need for medication or other support
  • children with hemodynamically significant congenital heart disease
  • children with anatomic pulmonary abnormalities or neuromuscular disorders
  • children with Down syndrome or other chromosomal differences

When RSV Immunization Is Not Recommended

RSV vaccines: People who have had a severe allergic reaction to an RSV vaccine or any of its ingredients should not receive that vaccine. Talk with your health care provider if you have a history of severe allergies.

RSV monoclonal antibodies: An infant or child should not receive an RSV monoclonal antibody if they have had a severe allergic reaction to that product or any of its ingredients.


When RSV Immunization May Not Be Needed or Recommended

  • Older Adults: An additional RSV vaccine dose is not recommended at this time if you have already received one.
  • Pregnant People: An additional dose of ABRYSVO is not recommended during a later pregnancy if you received it during a previous pregnancy. The infant should receive an RSV monoclonal antibody instead.
  • Infants Younger Than 8 Months: Most infants whose birthing parent received ABRYSVO at least 14 days before birth do not need an RSV monoclonal antibody.
  • Health Care Personnel: Working in a health care setting alone is not a reason to receive an RSV vaccine. Health care personnel should receive an RSV vaccine if they meet the age- or risk-based recommendations described above.
Where to get Immunized

If you have insurance:

  • Talk to your doctor or check with your local pharmacy to see what vaccines they offer.
  • Most health insurance plans cover the cost of recommended vaccines for children and adults.

If you are uninsured or underinsured:

  • Programs are available to help cover the cost of vaccines.
  • Children 18 years or younger may receive vaccines at no cost through the Vaccines for Children (VFC) Program if they are:
    • Eligible for or are enrolled in Medi-Cal
    • American Indian or Alaskan Native
    • Uninsured (do not have health insurance)
    • Underinsured (private health insurance does not cover the full cost of vaccines)
  • Adults who are uninsured or underinsured may be able to get free or low-cost vaccines at clinics enrolled in the Vaccines for Adults (VFA) program. For more information on who is eligible, read VFA Eligibility Based on Insurance Status.

Locating Vaccine Clinics:

  • A list of free and low-cost clinics in Los Angeles County.
  • Interactive county map to locate free and low-cost vaccine clinics.
  • Call 1-833-540-0473 (Public Health InfoLine) for a list of free or low-cost vaccine clinics. This includes Vaccines for Children (VFC) provider locations that serve Medi-Cal eligible children and uninsured or underinsured adults.
Keeping Record of Your Immunization Records

If you are unsure of your RSV immunization status, you can request a copy of your records.

To request your record:

If your vaccines are not listed, ask your doctor, pharmacist, or vaccine provider for a copy of your vaccine records. You can also ask them to add your vaccines to the California Immunization Registry (CAIR).

Other tips to find your records:

Additional Resources
Signage and Flyers
RSV Vaccine Facts (LAC DPH)

This FAQ is currently being updated (9/14/2026)
Expecting? Protect yourself and your baby against flu, RSV, whooping cough, and COVID-19 (CDPH)
Immunizations for a Healthy Pregnancy (CDPH)
Protect Yourself from Respiratory Viruses (CDPH)
Information for Providers
Clinical Presentation

Respiratory Syncytial Virus (RSV) causes a substantial burden of illness in the United States, particularly among infants, young children, older adults, and people with certain underlying medical conditions. RSV is the leading cause of infant hospitalization in the United States and can cause serious illness, hospitalization, and death in people at increased risk. The burden of RSV varies from season to season.

For current estimates of RSV-associated outpatient visits, hospitalizations, and death in the United States, see CDC RSV Burden Estimates

For current RSV activity and respiratory illness surveillance data in Los Angeles County, see LAC DPH RespWATCH.

In Infants and Young Children

RSV infection can cause a variety of respiratory illnesses in infants and young children. It most commonly causes a mild, cold-like illness but can also cause lower respiratory tract infections, including bronchiolitis and pneumonia.

Infants are at highest risk for severe RSV disease, particularly during the first months of life. Severe illness can occur in otherwise healthy infants as well as in children with underlying medical conditions.

Adults

In adults, RSV usually causes an upper respiratory tract infection. Symptoms may include rhinorrhea, pharyngitis, cough, headache, fatigue, and fever. Mild RSV illness typically resolves in 1–2 weeks.

RSV can also cause severe lower respiratory tract disease and lead to hospitalization, particularly among older adults and adults with underlying medical conditions.

Disease Reporting
  • See Reportable Communicable Diseases for reporting requirements for RSV.
  • Click here for more information on reporting a Vaccine Adverse Event.
  • Report adverse events when nirsevimab is administered alone, to FDA MedWatch or via phone 800-FDA-1088. When nirsevimab is administered with other vaccines, adverse events should be reported to VAERS.
Immunization Recommendations
Vaccines to Protect Older Adults
  • The American Academy of Family Physicians recommends a single dose of any FDA-licensed RSV vaccine for all adults aged 75 and older and adults ages 50–74 at increased risk of severe RSV
  • Three RSV vaccines are currently available for adults: AREXVY (GSK), ABRYSVO (Pfizer), and mRESVIA (Moderna). There is no preference for one RSV vaccine over another.
  • Adults who have already received an RSV vaccine should not receive another dose at this time.
  • Coadministration of RSV vaccine with other adult vaccines, including influenza and COVID-19, is acceptable.
  • For eligible adults who have not yet been vaccinated, the best time for RSV vaccination is late summer or early fall, before RSV usually begins to spread in the community.
  • Multiple studies have shown that RSV vaccines are effective in reducing severe RSV disease, emergency department visits, and hospitalizations.
Immunizations to Prevent Severe Disease in Infants

Maternal RSV Vaccine

  • American College of Obstetricians & Gynecologists (ACOG) recommends one dose of maternal RSV vaccine (Abrysvo) for pregnant persons at 32 through 36 weeks gestation (see Clinical Guidance). Pregnant people who are more than 36 weeks 6 days pregnant should not be vaccinated, as it is unlikely there will be enough time for antibodies to develop, cross the placenta, and protect the infant.
  • Administer RSV vaccine to pregnant persons from September through March 1st, so their infants will be protected against severe RSV disease at birth. Do not administer maternal RSV vaccine outside of this seasonal timeframe.
  • RSV vaccine can be co-administered with Tdap, COVID-19, and influenza.
  • Maternal RSV vaccine reduces the risk of severe infant outcomes caused by RSV by 82% within 3 months and by 69% within 6 months after birth.
  • Counsel patients regarding rare potential hypertensive disorders in pregnancy risk identified with RSV vaccine use during pregnancy.

Infant RSV Immunization

  • American Academy of Pediatrics (AAP) recommends RSV immunization (nirsevimab (Beyfortus, Sanofi) or clesrovimab (ENFLONSIA, Merck) for infants <8 months of age who are born during or entering their first RSV season, October through March, if:
    • The mother did not receive RSV vaccine during pregnancy, or
    • The mother’s RSV vaccination status is unknown, or
    • The infant was born within 14 days of maternal RSV vaccination.
  • Infants born during RSV season (October through March),should get an RSV immunization (nirsevimab or clesrovimab) within one week after birth – ideally during the birth hospitalization.

    Note:
    Depending on RSV activity in California, CDPH may recommend extending RSV monoclonal antibody administration period beyond March. Providers should monitor CDPH guidance and health alerts (LAHAN) for updates regarding any extension of the administration period. about the recommendations for the current RSV season.
  • Nirsevimab is also recommended for some children (8 – 19 months) who are at increased risk for severe RSV disease and entering their second RSV season. This includes:
    • Children born preterm, at <32 weeks, 0 days gestation, regardless of the need for medication or other support
    • Children with chronic lung disease of prematurity or to other significant neonatal conditions (e.g., meconium aspiration or congenital diaphragmatic hernia) who required medical support (e.g., chronic corticosteroid therapy, diuretic therapy, or supplemental oxygen) at any time during the 6-month period before the start of the second RSV season
    • Children with hemodynamically significant congenital heart disease (i.e., a defect that can result in symptoms and/ or cardiac chamber dilation)
    • Children with anatomic pulmonary abnormalities or neuromuscular disorders that put them at risk for severe RSV disease
    • Children with severe immunocompromise
    • Children with Down syndrome or other chromosomal differences placing them at higher risk of severe RSV disease
    • Children with cystic fibrosis who have either 1) manifestations of severe lung disease (previous hospitalization for pulmonary exacerbation in the first year of life or abnormalities on chest imaging that persist when stable), or 2) weight-for-length less than the 10th percentile
    • American Indian or Alaska Native children
  • Nirsevimab (BEYFORTUS™) is at least 80-90% effective in preventing RSV-related hospitalizations in infants. Studies also shown that clesrovimab (ENFLONSIA™) has similar effectiveness.
Monoclonal Antibody Doses
Age of Administration Dose Comments
< 8 months or born shortly before or during RSV season Nirsevimab
Infants < 5kg (<11 lbs) 
50mg (IM)
purple plunger

Infants ≥ 5kg (≥ 11 lbs)
100 mg (IM)
light blue plunger

Clesrovimab
105mg (IM) single dose syringe
For infants born during RSV season (October - March), administer within one week of birth – preferably before discharge.
Dose can be administered along with the Hep B birth dose.

Infants born before RSV season (April – September) should be vaccinated as soon as possible between October and March.
8 – 19 months entering their 2nd RSV season Nirsevimab
200 mg (IM) [2 x 100mg IM injections light blue plunger administered on the same day]
Dose can be co-administered with other age – appropriate immunizations, i.e., COVID and flu.

Only nirsevimab is recommended for infants 8 – 19 months entering their second RSV season.
Vaccine Reporting, Storage, and Handling

Administration Data: California healthcare providers are required to report data on all valid immunizations that they administer to their patients into the California Immunization Registry (CAIR) within 2 weeks of administration per AB 1797.

Administration Errors: Healthcare providers are strongly recommended to report all vaccine administration errors to the Institute for Safe Medication Practices.

Adverse Events: Healthcare providers are required to report any adverse event on the reportable events list to the Vaccine Adverse Event Reporting System (VAERS) per HR 5546.

For RSV monoclonal antibody products (e.g., nirsevimab, clesrovimab), when not co-administered with other vaccines, VFC providers should report all suspected adverse reactions to MedWatch. Providers should report suspected adverse reactions following co-administration of RSV monoclonal antibody products with any vaccine to the Vaccine Adverse Event Reporting System (VAERS).

Storage and Handling: For general recommendations and guidance access the Vaccine Storage and Handling Job Aids.


Adobe Reader

Note: PDF documents on this site were created using Adobe Acrobat 5.0 or later. Document functionality may be reduced if you are using an earlier version (4.x or less). Get the latest version of Adobe Acrobat.


Public Health has made reasonable efforts to provide accurate translation. However, no computerized translation is perfect and is not intended to replace traditional translation methods. If questions arise concerning the accuracy of the information, please refer to the English edition of the website, which is the official version.

Los Angeles County Seal: Enriching lives through effective and caring services